Thymosin alpha-1 research peptide at Peptide Coalition
The encouraging earlier sepsis result deserves to be remembered. The larger negative trial deserves to change the conversation.
Stations
Sepsis: ETASS, then TESTS
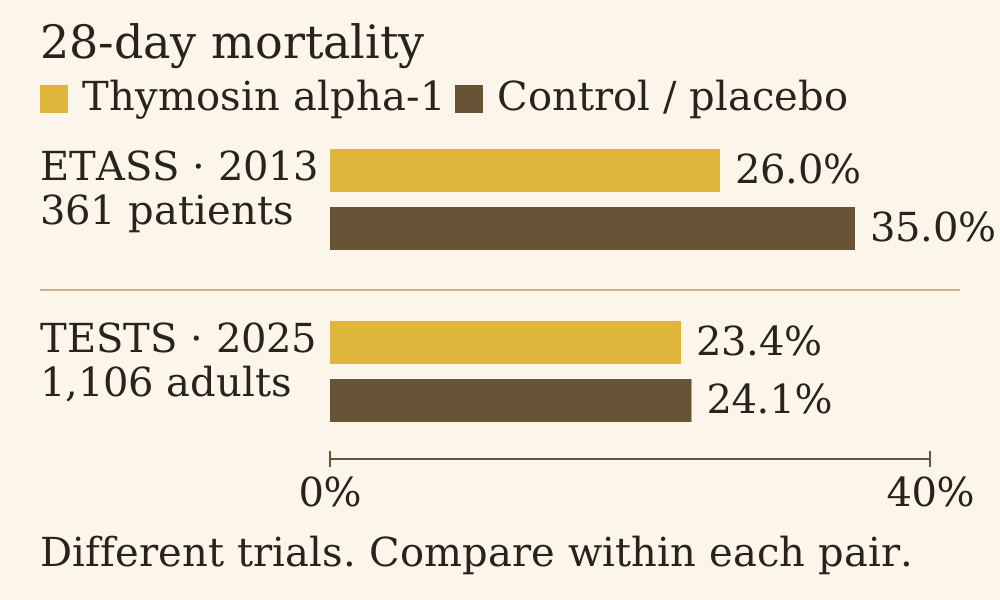
ETASS enrolled 361 patients with severe sepsis. At 28 days, all-cause mortality was 26.0 per cent in the thymosin alpha-1 group and 35.0 per cent in controls. The nonstratified P value was 0.062; the log-rank P value was 0.049. That numerical difference earns my curiosity. The differing statistical tests warrant restraint.
The phase 3 TESTS trial then enrolled 1,106 adults with sepsis across 22 centres in a double-blind, placebo-controlled design. Mortality was 23.4 per cent with thymosin alpha-1 and 24.1 per cent with placebo. The hazard ratio was 0.99, with a 95 per cent confidence interval of 0.77 to 1.27 and P equal to 0.93. It found no statistically significant reduction in 28-day all-cause mortality.
The chart compares the reported percentages within each trial. The control groups had different mortality rates, so its bars cannot turn two separate studies into a head-to-head comparison. For sepsis, my judgement follows the larger blinded result.
Immune biology
Thymosin alpha-1 is a twenty-eight-amino-acid peptide cleaved from prothymosin alpha. Its synthetic version, thymalfasin, has the same sequence. The comprehensive review describes its immune-modulating activity at the junction between innate and adaptive immunity: dendritic cells help present material to T cells, which develop a more targeted response.
This biology can involve both effector responses and regulatory activity. “Immune support” sounds much tidier than the system being influenced. I distrust the shorthand “immune support” when it turns an intricate mechanism into a reason to expect clinical improvement.
Thymalfasin is approved in more than thirty-five countries, but it is not approved for marketing in the United States. The international history and the null sepsis result coexist. A regulatory fact about a drug's availability cannot settle a new question about an outcome.

Other immune settings
A retrospective study of 76 patients with severe COVID-19 associated treatment with lower mortality, 11.11 per cent against 30.00 per cent, with P equal to 0.044. It also reported increased T-cell numbers in patients with severe lymphocytopenia and changes in markers of T-cell exhaustion. Retrospective treatment groups can differ in ways the analysis cannot fully resolve; the association warrants a more cautious interpretation than a randomised result.
The cancer-therapy reappraisal discusses thymosin alpha-1 as an adjunct alongside chemotherapy and immunotherapy, including melanoma, hepatocellular carcinoma and lung cancer. Its account combines clinical and preclinical work. These combination settings ask their own questions about immune activity and tolerability. TESTS cannot answer them, and they cannot rescue a sepsis claim that TESTS failed to support.
Thymosin and thymopoietin
The identity covered here is thymosin alpha-1, also called thymalfasin. The review specifies its relationship to prothymosin alpha. I cannot carry alpha-1 findings over to thymopoietin without a study of that molecule. Similar-looking names offer too little basis for combining clinical histories.
The same care applies to a “thymosin alpha-1 third party tested” claim. None of the studies on this page certifies the identity, purity, concentration or sterility of a particular research sample. No particular batch can receive a verdict from this set of clinical papers. The clinical history of thymalfasin and the documentation for a sample answer different questions.
Resilience reports
People describe fewer respiratory infections, more resilience, steadier energy, or simply feeling no difference. These are anecdotal accounts rather than clinical evidence of improved immunity. Local redness or stinging, an achy feeling and tiredness also occur in community descriptions.
The comprehensive review reports tolerability dominated by local injection-site reactions. Pregnancy and lactation data are limited. Immune stimulation raises theoretical concerns in autoimmune disease and in solid-organ transplant recipients whose immune response is deliberately suppressed. Those concerns follow the biology; they are not established rates of harm in those populations.
The comparison page places this mixed clinical history beside the other members. TESTS has left me less hopeful about sepsis because a stronger trial was run. That is a useful outcome of research, even when the medicine fails to deliver the hoped-for one.